Recording a UTI consultation
Record a UTI consultation guided by your jurisdiction's protocol, moving through it as a wizard or a single scroll, then print the patient summary and any GP referral.
This UTI consult is a structured encounter for an uncomplicated urinary tract infection, delivered under your expanded scope of practice. Light guides it with prompts and reference material based on the protocol that applies in your jurisdiction, surfaces the eligibility and screening criteria to consider, and assembles the record and documents from what you record.
The prompts and reference material are set by your site's jurisdiction, chosen automatically – you don't pick it. The consult is supported in the ACT, NSW, Queensland, South Australia, Tasmania, and Western Australia. It isn't available in Victoria: Light isn't currently approved software for the Victorian Community Pharmacist Program, and the encounter can't be completed at a Victorian site.
Before you start
UTI consults are part of the expanded scope of practice, for pharmacists who have completed the approved training and who meet the requirements that apply to the service in their jurisdiction. Depending on your jurisdiction, these may include:
- completing the relevant training
- meeting the applicable practice standards and protocol
- sharing a record of supply with the patient's usual medical practitioner or practice, where the patient has one and consents, within the timeframe the protocol sets
- having a suitable private space to conduct consultations
These requirements are set by the protocol and practice standards for your jurisdiction, not by Light. Confirm the current requirements that apply to you before you deliver the service. See How the platform uses clinical protocols and standards.
Some jurisdictions also require your individual healthcare provider identifier (HPI-I) to be recorded. You can add it against your own profile at Settings›Team – open your profile and add your HPII on the Identifiers page.
Starting the service
There are three ways to start:
- From Services – go to Services, select Add, choose the UTI Consult service, then select an existing customer or add a new one.
- From the customer – open the customer's record, select Services, then choose Add service and select the UTI Consult service.
- From a booking – if the patient booked in for the consult, start the encounter from their booking.
Choosing how you work through it
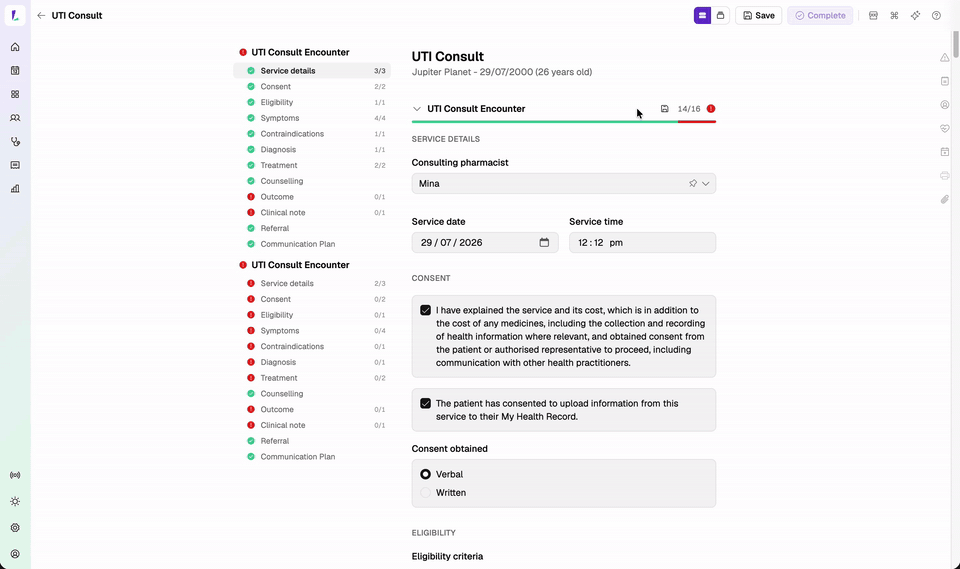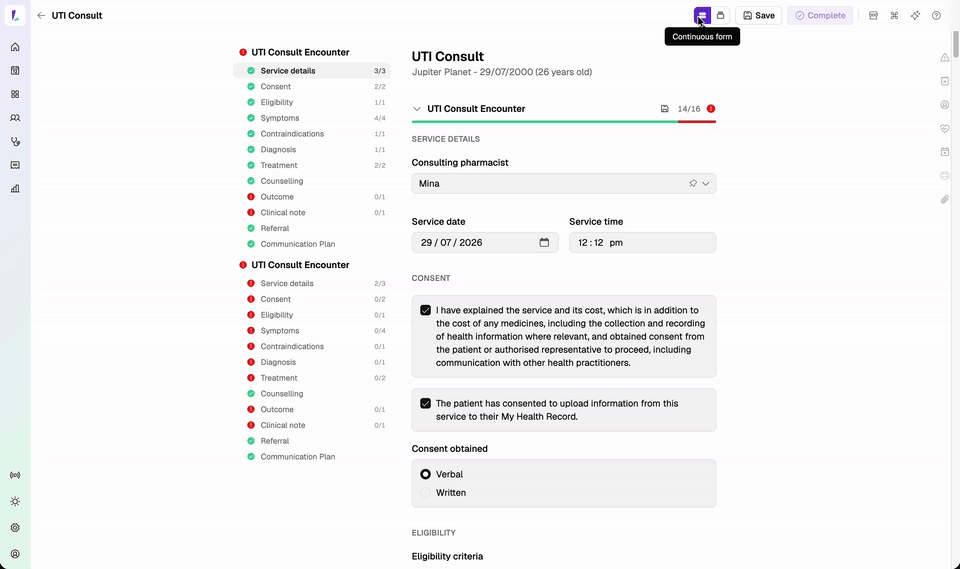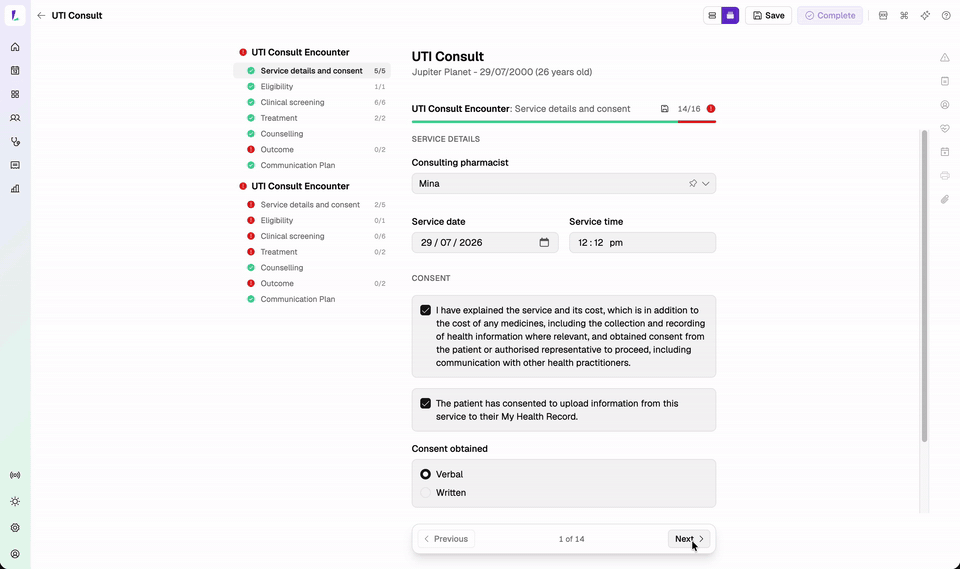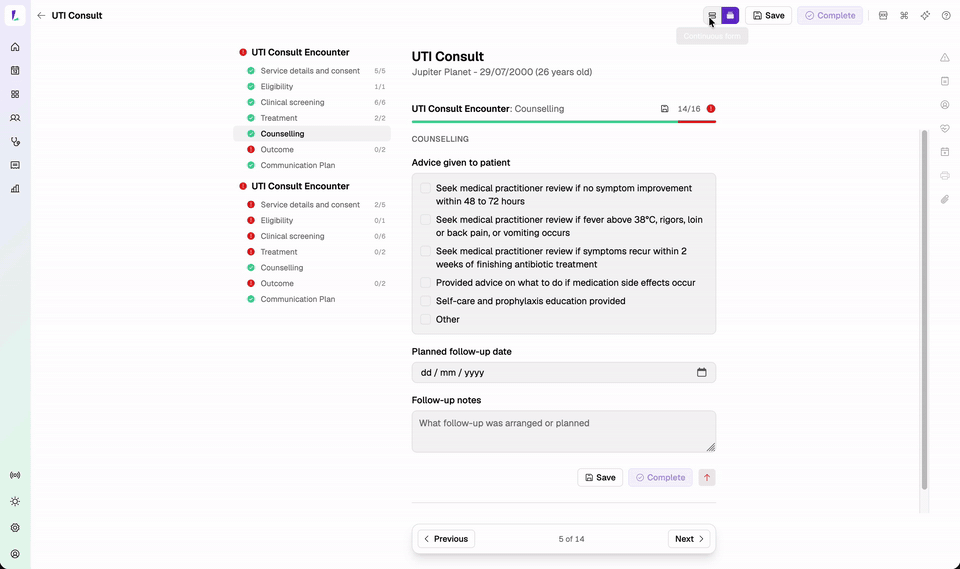
UTI consults let you choose how you move through the encounter. In the encounter header, the Form display control switches between:
- Continuous form – one scrolling page, with a section rail down the left to jump between sections.
- Step-by-step form – a guided wizard that takes the sections a screen at a time.
Pick whichever suits you – the record is the same either way. Both modes show the section rail, so you can see where you are and what's left.
The reference panel
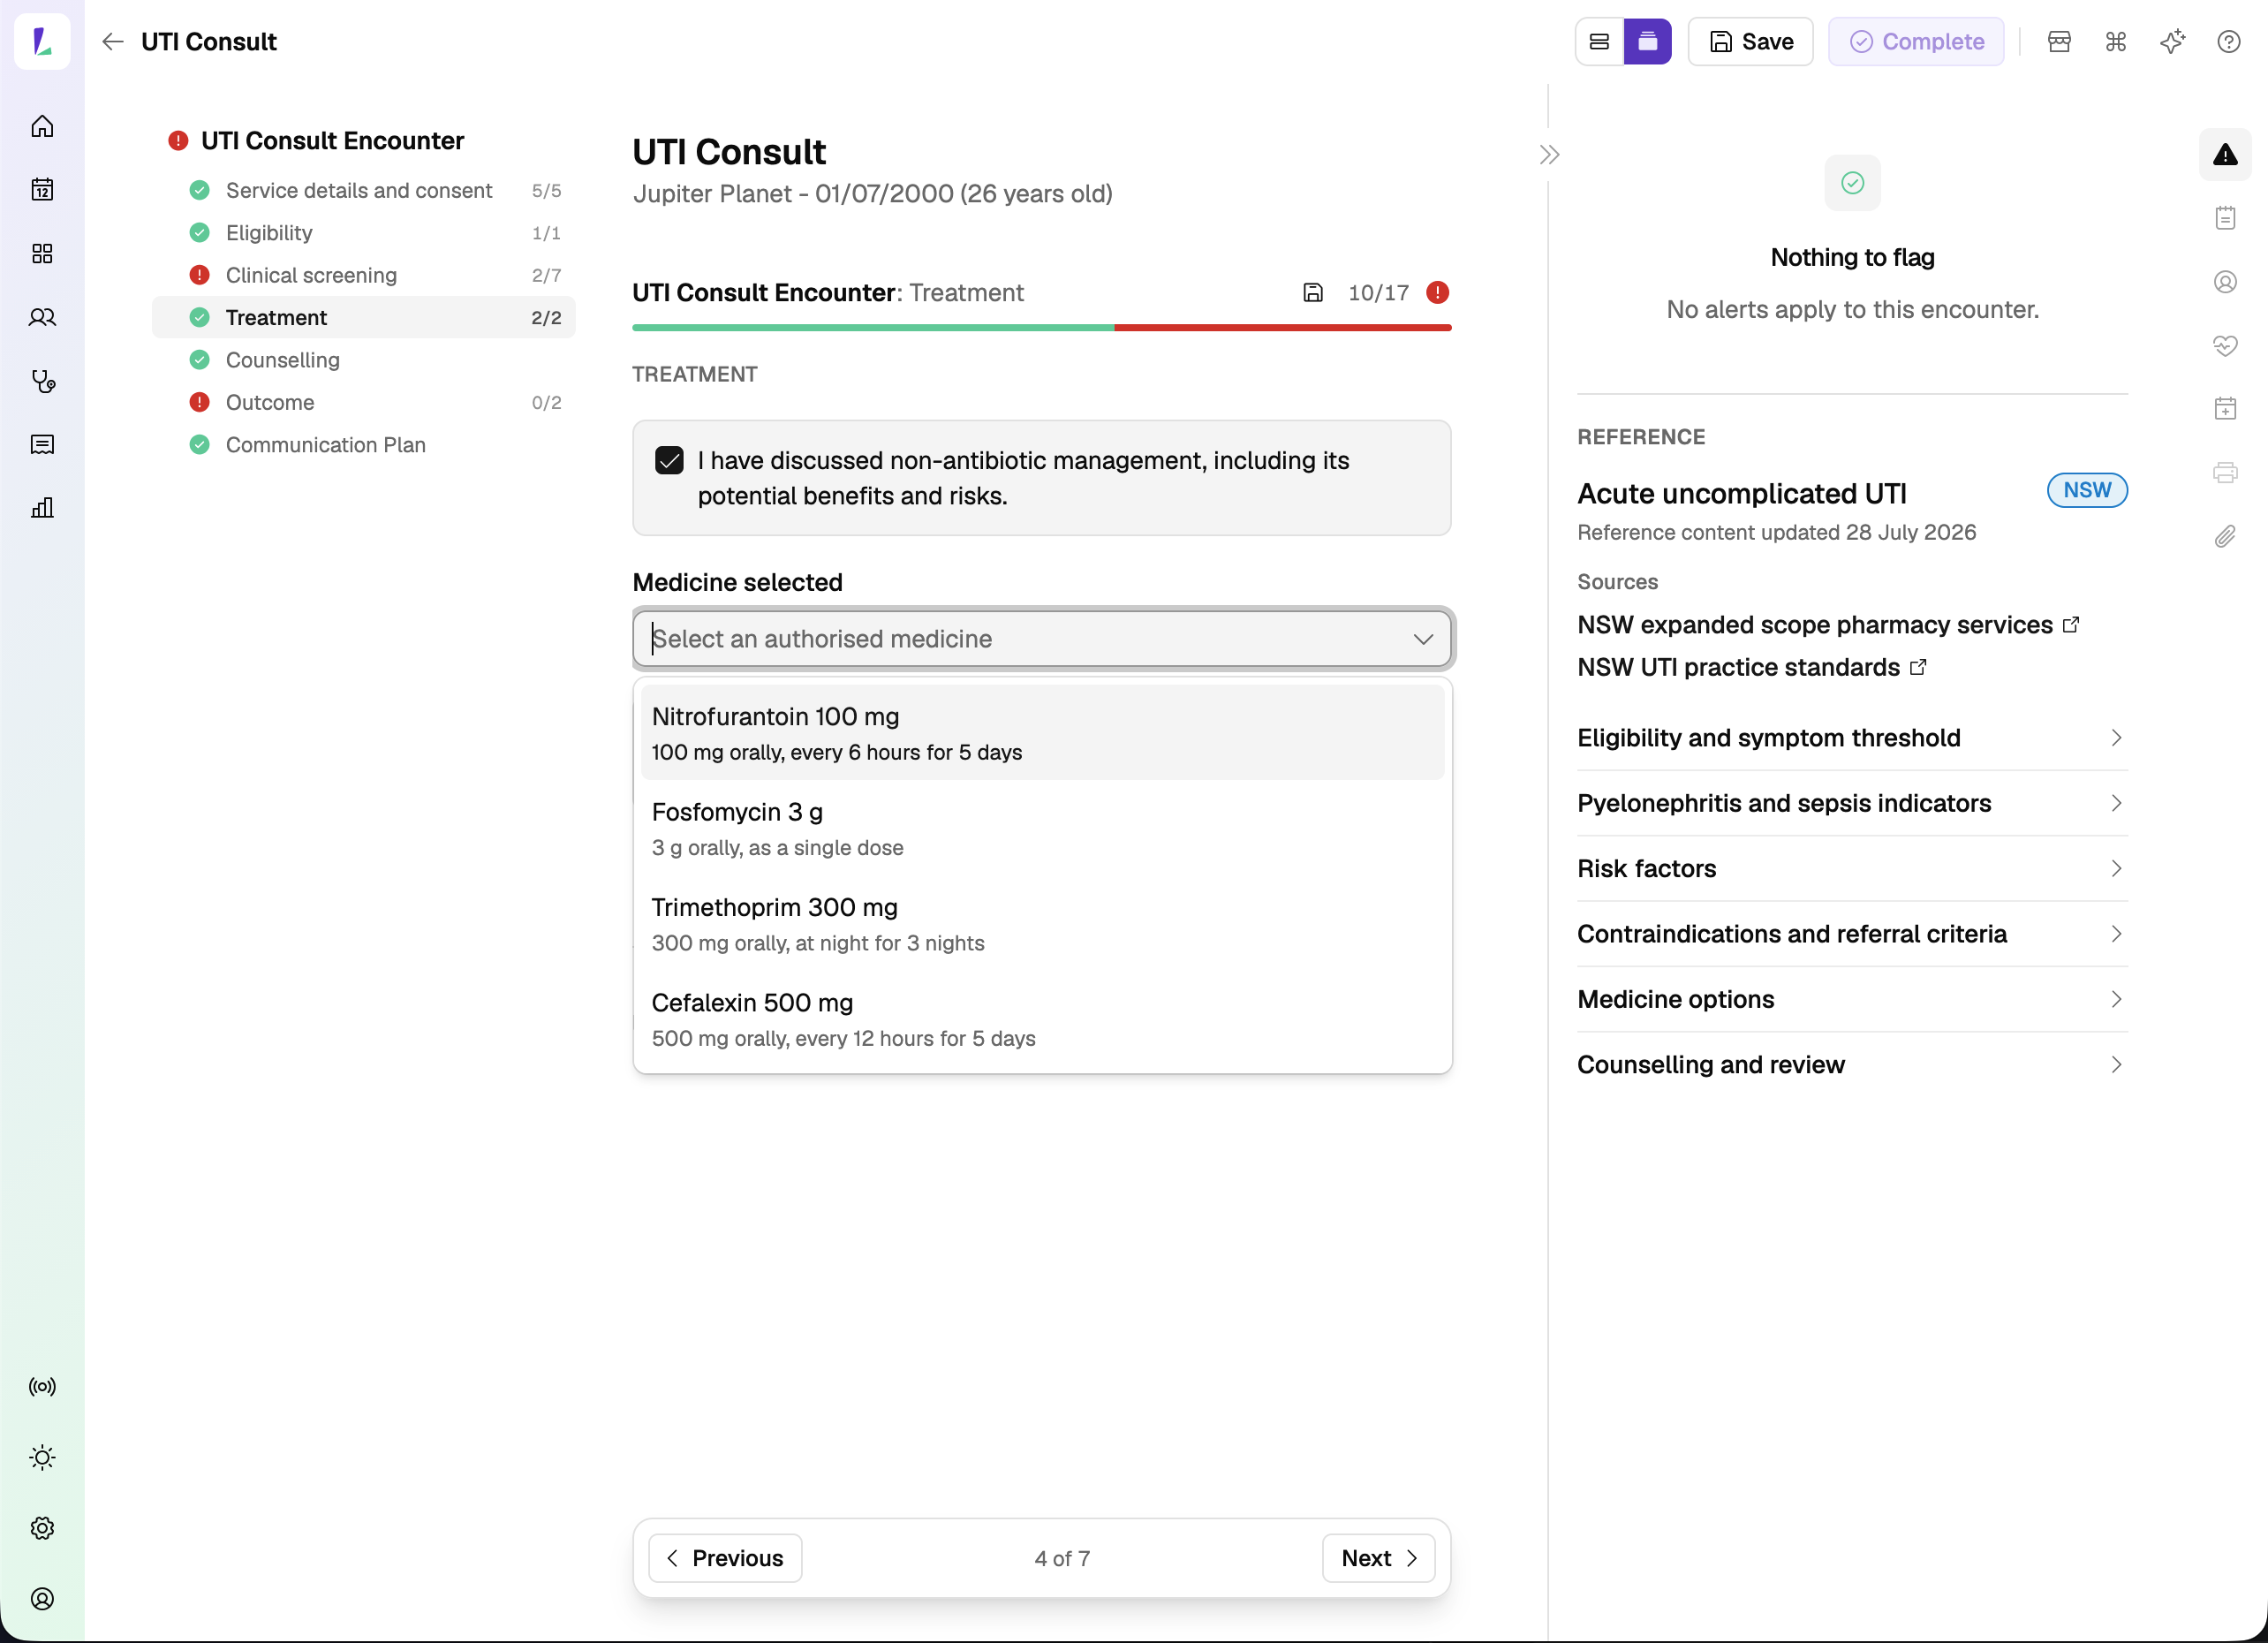
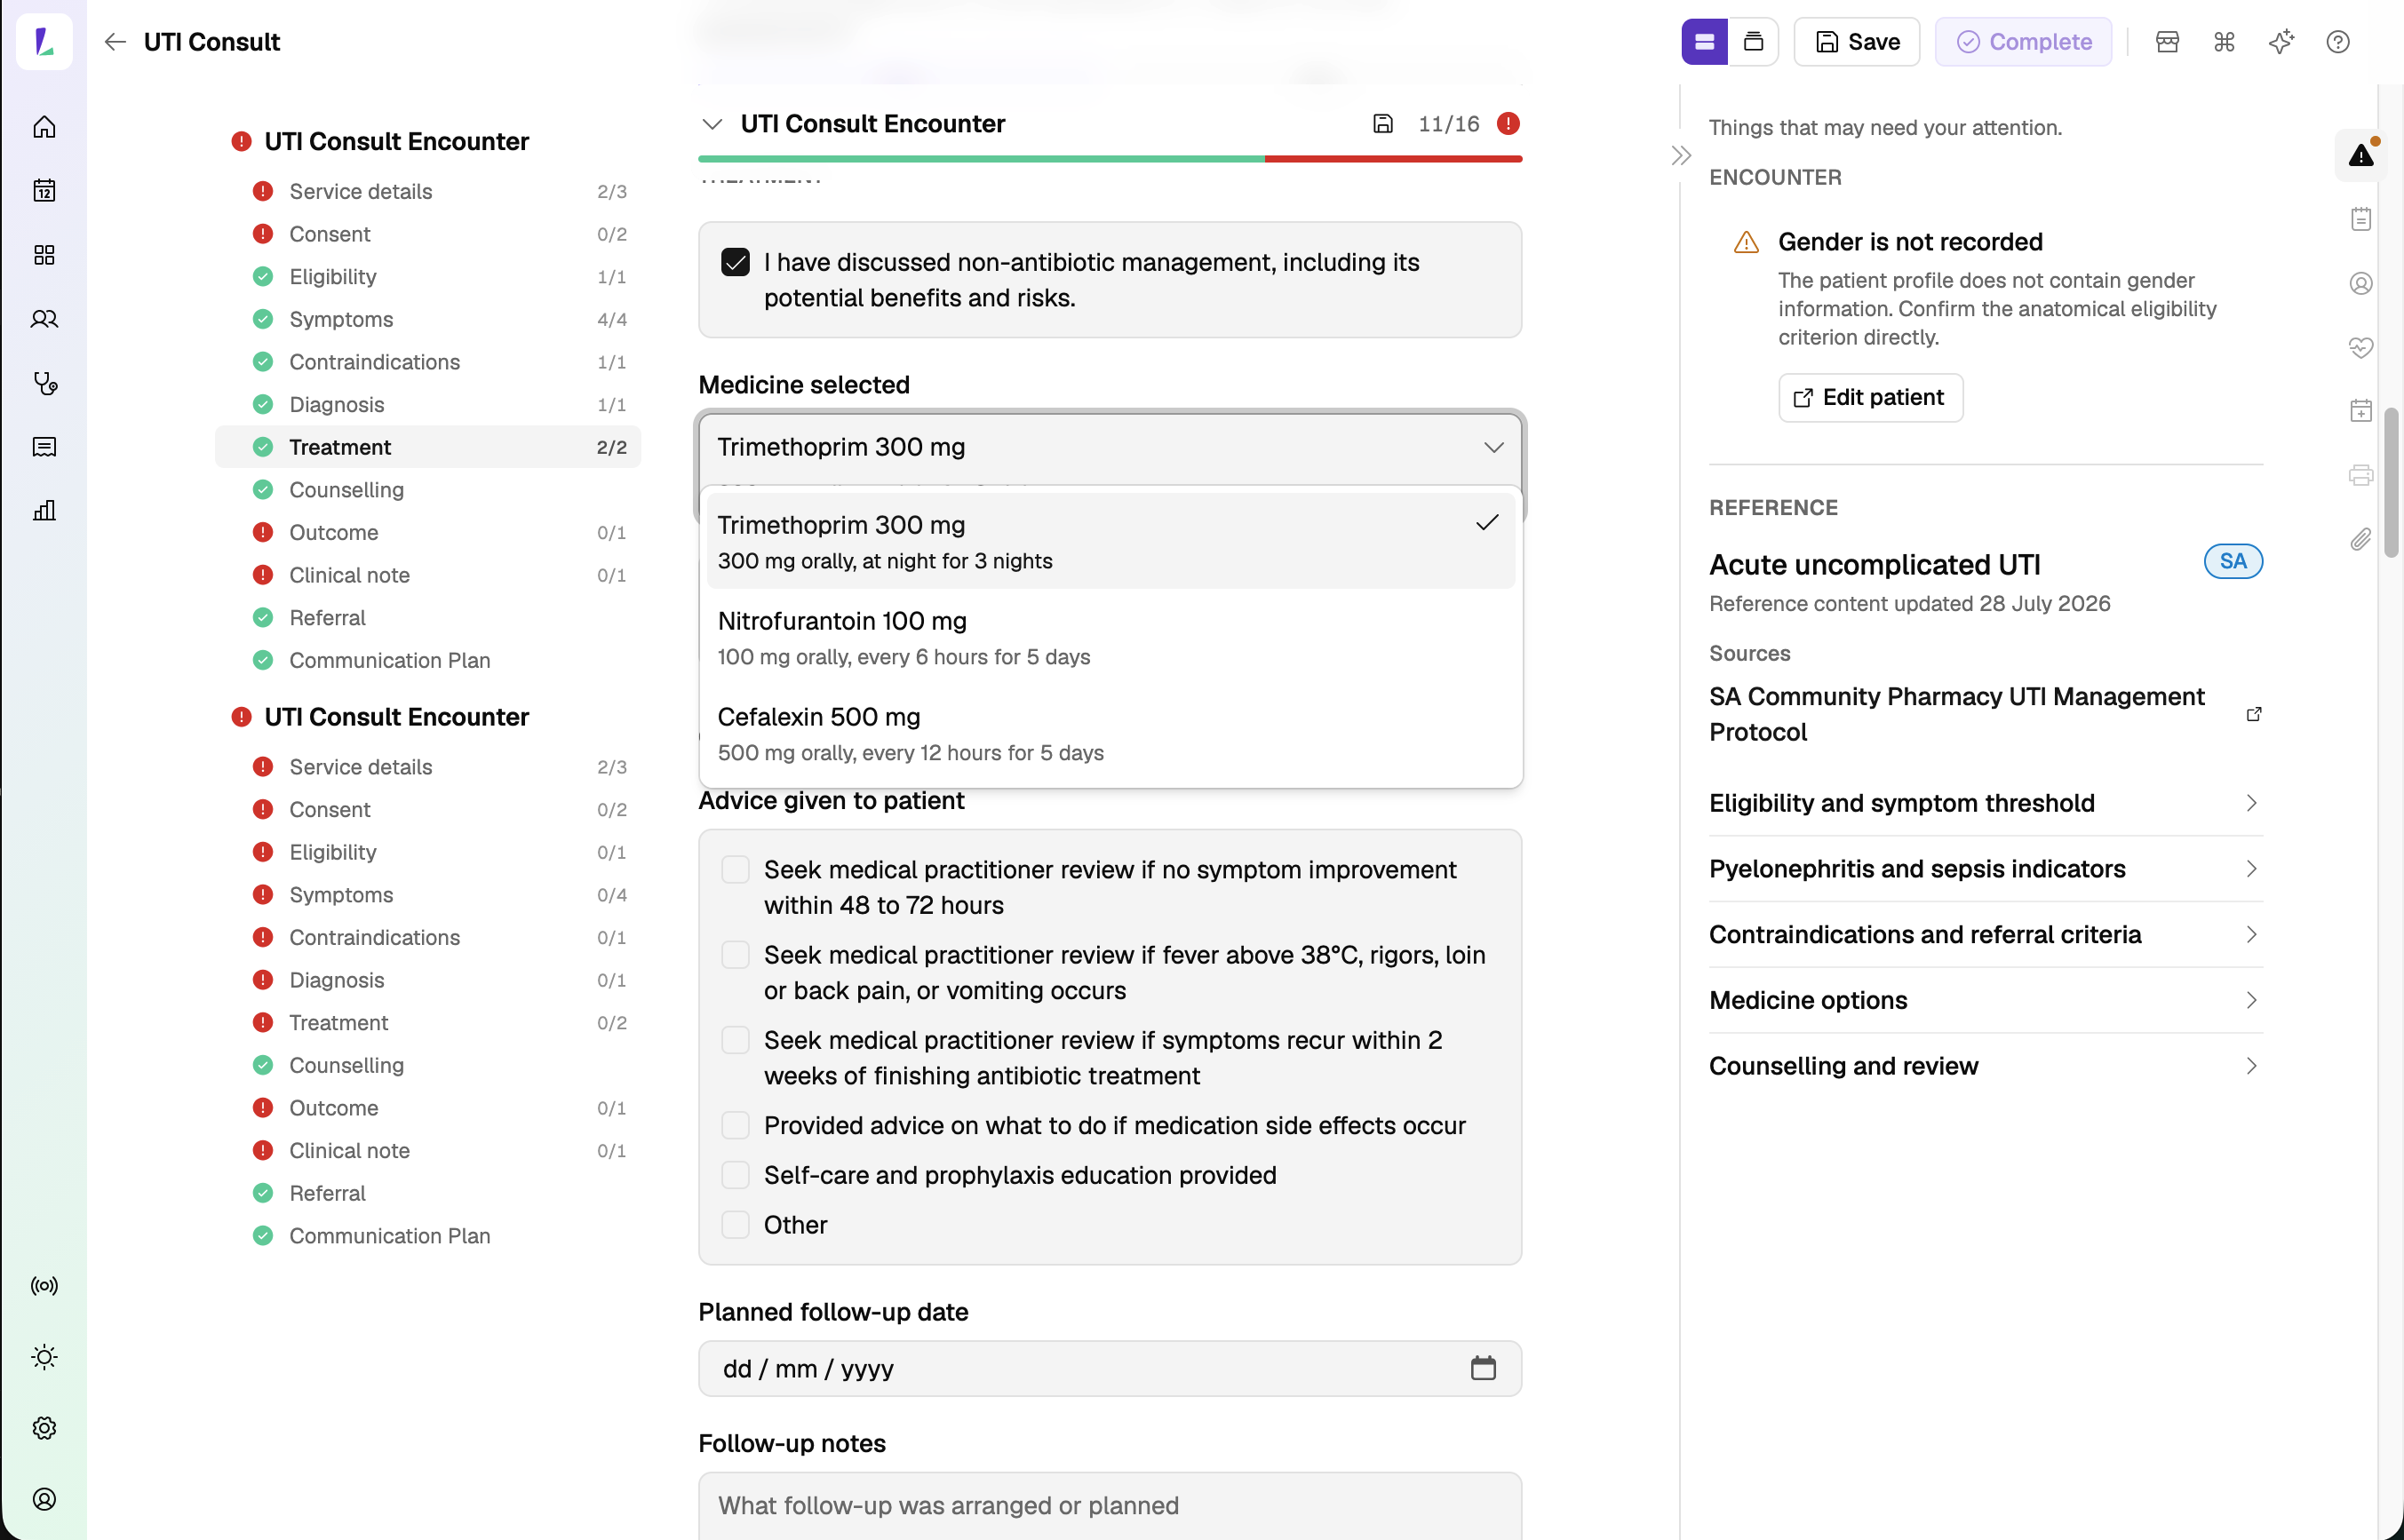
The Reference panel sits beside the encounter with the clinical reference for your jurisdiction. Each topic carries a jurisdiction badge (for example, NSW), a Last reviewed date, and a Sources list linking to the governing protocol and guidelines. Keep it open as you work – it's the guidance behind the prompts.
The reference reflects its sources as at a point in time, not a live feed. For where the content comes from and what stays your responsibility, see How the platform uses clinical protocols and standards.
Working through the consult
The consult moves from consent, through eligibility and clinical screening, to diagnosis, treatment, and the outcome. In step-by-step mode these group into: Service details and consent, Eligibility, Clinical screening, Treatment, Counselling, Outcome, and Communication Plan.
Record eligibility against the Eligibility criteria for your jurisdiction – tick each criterion the patient meets, then record whether the patient meets the service eligibility criteria overall. The screening sections – pyelonephritis, sepsis, contraindications, and the provisional diagnosis – work the same way.
The criteria, contraindications, risk factors, and medicine options presented all follow your jurisdiction's protocol – so what you see reflects the protocol for your state, and differs where jurisdictions differ. For example, the first-line medicine offered under the NSW protocol differs from the one under the SA protocol:
When a criterion isn't met
If you record that the patient doesn't meet the eligibility criteria – or a screening step flags pyelonephritis, sepsis, a contraindication, or that a provisional UTI diagnosis can't be made – the consult skips the treatment steps and takes you straight to Outcome and Referral. The skipped sections are marked "skipped after screening" in the section rail.
Light records the outcome and reroutes you; it doesn't stop you completing the record. The judgement stays yours – see How the platform uses clinical protocols and standards.
Recording the outcome and referral
In Outcome, record the outcome of the consult. In Referral, record the referral pathway, along with your clinical note and communication plan. The options in each field follow your jurisdiction's protocol.
If there's more you'd like to capture than the structured fields hold, add it to the Clinical note, the Notes panel on the right, or as an attachment.
Completing and printing
Complete the encounter to save the record. You can then print:
- Patient Summary – for the patient.
- GP Referral – where you've referred the patient on.
Both print on your pharmacy letterhead and can carry your signature.
Recording responsibility
This article explains how to record this encounter in Light. Practitioners remain responsible for delivering the service in accordance with applicable clinical, program and jurisdictional requirements and for maintaining a complete and auditable record. See Recording Encounters in Light and How the platform uses clinical protocols and standards.
Authorities, practice standards, and protocols can change at any time, without warning or notice to software vendors. The content in Light may not reflect the most recent version at the time you use it. Always confirm against the current published source before you rely on it.